Why does your foot suddenly seem to drag or catch on the floor when it never used to? Why does a walk that felt automatic for years now take real concentration? The answer isn’t a lack of effort. It’s multiple sclerosis (MS) interrupting the nerve signals that control your legs, and it’s a documented, well-studied part of the disease.
Understanding why this happens is the first step, and there’s more you can do about it, and more support available, than most people realize.
Let’s dive in!
Table of contents
Why MS Changes the Way You Walk
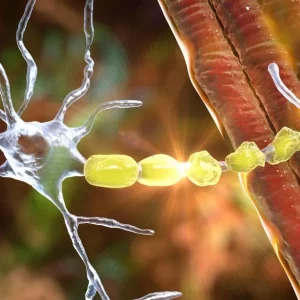
MS damages the myelin coating around nerve fibers in the brain and spinal cord. Myelin is like insulation on a wire. It helps electrical signals travel quickly and cleanly.
When it’s damaged, the signals telling your leg muscles when to move get delayed, weakened, or scrambled. Your brain also gets less clear feedback about where your foot actually is.
That’s why gait problems are so common in MS. Research shows that within 10 to 15 years within disease onset , roughly 80% of people with MS have some kind of walking difficulty. It’s driven by a mix of muscle weakness, spasticity (muscle tightness or stiffness), fatigue, and poor balance.
Studies find that people with MS tend to walk slower than people without MS. They also take shorter, wider steps. And they spend more time with both feet on the ground at once.
That extra time with both feet down isn’t random. It’s your nervous system trying to buy itself more stability with every step. This is a natural compensation your body uses to maintain stability.
The Three Gait Patterns Behind MS Walking Changes
Not everyone with MS walks the same way, because MS doesn’t damage every nerve pathway equally. Kinematic research has identified three common patterns:
- Spastic-paretic gait. Stiff, weak legs that are hard to lift and swing forward smoothly.
- Ataxic gait. Uncoordinated, unsteady steps caused by damage to the cerebellum, the part of the brain that fine-tunes balance and movement.
- Unstable or sensory gait. Steps that feel unreliable because you can’t fully sense where your foot or leg is in space.
Knowing which pattern fits your own walk matters. It points you toward the right strategies and tools to try first.
Ask your physical therapist which pattern shows up most in your gait. It’s a useful, specific question for your next appointment.
Foot Drop: The Most Common Walking Change in MS
One of the most common individual symptoms behind MS gait changes is foot drop: difficulty lifting the front of your foot as you swing your leg forward. It’s why so many people with MS describe catching their toe on the carpet, a curb, or their own other foot.
Foot drop happens when weak signals fail to fully activate the muscles at the front of your shin. Those muscles lift your foot at the ankle, a motion called dorsiflexion. Without enough lift, your toes drag as you swing your leg forward, which raises your risk of tripping.
What Many People Get Wrong: Foot drop isn’t a sign that your leg muscles are “wasting away” or that walking is only going to get harder from here. It’s a signal transmission problem, and there are tools designed specifically to work around it.
Mobility Aids That Can Help You Walk with More Confidence
Using a mobility aid isn’t a step backward. It’s a legitimate way to keep moving safely, conserve the energy MS fatigue already taxes, and stay active enough to keep working on your walking, not less able to. Here’s what the research supports:
- Ankle-foot orthoses (AFOs). A lightweight brace worn inside your shoe that holds your foot at a better angle, reducing toe drag from foot drop and improving overall gait pattern.
- Functional electrical stimulation (FES). A small device that sends an electrical pulse to your foot muscles at the right moment in each step. A meta-analysis of 19 studies found FES has a real, measurable effect on walking speed over short distances. The improvement was largest in people walking slower than 0.8 meters per second. That’s about the speed you need to cross a street safely.
- Canes. Helpful for milder balance issues. A four-point (quad) cane offers extra stability if your balance concern is more significant.
- Trekking poles. A study comparing assistive devices found trekking poles improved walking measures. Some users also felt less stigma using poles than a cane, worth knowing if self-consciousness has kept you from trying an aid at all.
- Walkers. Provide the most support. Worth considering when weakness or balance issues make a cane feel unsteady. A walker lets your arms share some of the work your legs can no longer fully manage alone.
The right aid depends on your gait pattern, your fatigue level, and how your symptoms shift through the day. Make this choice with your physical therapist, not by guesswork.
Why Gait Training Still Matters, Even with an Assistive Device
An assistive device manages a symptom in the moment. Gait training works on the underlying pattern itself, and both have a real place in your care.
Your nervous system builds and strengthens pathways through repeated, hands-on practice. This is called neuroplasticity. Walking practice, done consistently, teaches your brain and spinal cord to fire the right muscles at the right time again. It works even when the signal is weaker than it used to be.
The research backs this up. A pilot randomized trial tested robot-assisted gait training against intensive overground walking training in people with MS. Both significantly improved walking speed, and neither clearly beat the other. Separately, high-intensity interval training has shown promise for improving exercise capacity and reducing MS-related fatigue. Whether it is clearly better than steady, moderate-intensity exercise for walking speed specifically is still being studied..
The common thread isn’t one magic exercise. It’s consistent, challenging, walking-specific practice. A short walking session most days of the week will do more for your gait over time than one exhausting effort every few weeks.
Moving Forward
MS gait changes can feel like they arrived overnight. But they follow a pattern that’s been studied for decades, and there’s a real toolkit for responding to it. Your walking pattern today isn’t fixed. Weakness, spasticity, foot drop, and balance issues each respond to their own combination of assistive devices and targeted practice.
Talk with your neurologist or physical therapist about which change matters most right now: spasticity, foot drop, imbalance, or fatigue. Then ask which mobility aids or training approaches are worth trying first. Small, specific questions like “could an AFO help my foot drop” or “would gait training help my endurance” tend to get you further than a general “what should I do about walking.”
We hope you enjoyed this article and subscribe to our newsletter for weekly articles just like this delivered straight to your inbox — subscribe here.